Harmonious Healing: The Prostate: Diagnosis & Treatment
Due to the propensity of the prostate cancer epidemic we wish to bring the reader a very in-depth article to assist men and their families who are navigating their way through the language, diagnosis and treatments used for prostate issues and prostate cancer by the modern medical system. We know that due to the political and economic strength of the modern medical system it is the most widely used and relied upon medical system in the modern world. We also tend to present an alternative understanding to prostate health as well as treatments and preventative measures from the traditional natural medical field. This is the second installment of a three part series of articles.
Diagnosis
DRE
The Digital Rectal Exam (also DRE) is the primary method of diagnosing prostate health. Being the most common method of diagnosis many men may be familiar with this examination. It is done within routine physical examinations. The patient is bent over a table or lying on one side and holding his knees close to his chest. The doctor inserts his gloved, lubricated finger into the patient's rectum and feels the side of the prostate through the rectum wall that faces the anus. By feeling the prostate gland the doctor can tell whether the gland has any bumps, irregularities, soft spots, or hard spots that require additional tests. Cancer of the prostate feels very hard. This procedure is invasive and uncomfortable, but it is very brief and in terms of prostate procedures it is one of the most harmless.
PSA Blood Test
In 1986 the Food and Drug Administration approved the first PSA (Prostate Specific Antigen) blood test, this was a turning point in prostate cancer detection. It is for this reason that researchers remain unsure as to the true rate of growth of prostate cancer cases before 1986 and after. We should realize however that in 1991 the PSA test was standardized and we have still noticed an incline in prostate cancer diagnosis since that time. These statistics paired with the nationality factor and the drastic difference in prostate cancer saturation point to a health crisis of epidemic ramifications that cannot be denied.
Though invasive, the PSA test is a simple procedure. A doctor takes blood through a tube in your arm. The blood is sent to a lab where the levels of protein specific to the prostate in the blood is determined and the results are returned to the patient usually in just a few days. In the past, the normal PSA level was between 0 and 4.0 nanograms per milliliter. Today the level that is normal is constantly being challenged by progressive doctors and researchers. With the normal level of anything below 4.0 ng/ml many men suffering from prostate cancer can be missed because men who test with a PSA level between 0 & 4 can still have cancer cells in the prostate gland. In fact 25% of prostate cancer patients will test with a PSA level between 0 & 4 ng/ml. Also only about 25% of men with a PSA level between 4.1 & 10.0 ng/ml are diagnosed with prostate cancer in the subsequent testing (explained below). The rest had elevated PSA levels due to prostatitis, BPH or laboratory error. This means that many men are undergoing unnecessary biopsies for no other reason than an inaccurate setting of normal PSA levels, or an inadequate understanding of the relationship between prostate specific proteins in the blood and prostate cancer.
Many doctors believe that more appropriately any PSA level above 1.0 ng/ml should be considered abnormal but it should point to prostatitis and BPH issues instead of looking over them for prostate cancer. BPH and prostatitis are serious issues that cannot be ignored and often are understood to be on the path to prostate cancer if not attended to effectively. Other doctors are pushing for age-specific normal levels. They suggest, on average, that men 50 years or older should have an abnormal PSA level above 2.0 ng/ml and men between 70 and 79 can have a normal PSA level up to 6.5 ng/ml without prostate cancer.
Urinalysis
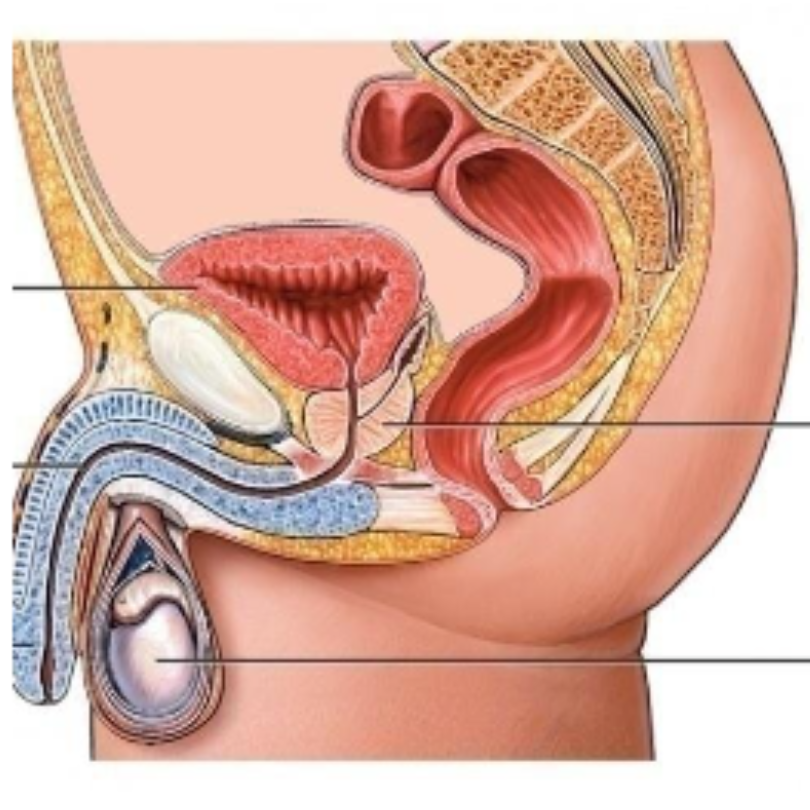
Urine samples are also taken in order to measure the bacteria and infection-fighting white blood cells or nitrate, a by-product of a bacterial infection present in the urine. If bacteria is found the patient may be asked to urinate into two or three containers so that doctors can determine the location of the infection. If signs of infection are found only in the first container then the infection is likely to be in the urethra. The nurse or doctor may also include a prostate massage in the middle of the urine sample and if signs of infection remain than it is likely that the patient is dealing with bacterial prostatitis. Small traces of blood could also be found in the urine which could point to kidney or kidney stone issues.
Transrectal Ultrasound
If prostate cancer is suspected, your doctor will recommend more serious and more dangerous diagnostic procedures. One of these procedures is the transrectal ultrasound (also known as the TRUS). In this procedure, the doctor or technician inserts a probe slightly larger than a pen into the rectum. The probe directs high frequency sound waves at the prostate, and the echo patterns form an image of the gland on a television monitor. The image shows how big the prostate is and whether there are any irregularities. A hypoechoic return (where the echo returning to the probe is different in a certain spot, than that returned from the majority of the gland) points to malignancy, however overall TRUS fails to unequivocally identify tumors.
Biopsy
The biopsy is done with a TRUS. The probe is inserted into the rectum as in the normal TRUS procedure and the biopsy gun is threaded through the probe. When the gun is fired the biopsy needle punctures through the rectal wall into the prostate gland. Using the ultrasound machine to guide the process the biopsy needle collects several samples of flesh from the prostate (from 6 or more flesh samples). This method of going through the rectum is very risky because puncturing the rectum with the biopsy needle allows the blood stream around the prostate gland (which is already compromised) to be contaminated by the fecal matter that is found in the rectum. Enemas are used to try to avoid this situation but many side effects still result from rectal biopsy. For this reason, many places around the world choose to biopsy patients through the perineum (the area between the testicles and the anus) to get to the prostate. US doctors and technicians do the easier rectal biopsies.
There are many serious side effects of prostate biopsies and one should be aware of them all before proceeding. About 50% of men have blood in their semen for days to weeks after the procedure, while 25% will have blood in their urine. A few men will have rectal bleeding. All patients will experience pain after the procedure for a while which is usually treated with painkillers and antibiotics in hopes of stopping infections. Some will experience bacterial prostatitis from the rectal bacterial contamination. A few men--less than 1%--will be completely unable to urinate after biopsy. Some experience fainting from drops in systolic blood pressure and others experience pain during bowel movements, fevers and/ or chills. Biopsies can also miss the site of cancer and then doctors may want to do repeated biopsies. In the end, many men end up dealing with unnecessary severe side effects due to raised PSA levels who do not even have prostate cancer.
Biopsy is also widely known to be pretty dangerous as far as cancer diagnosis is concerned. As explain above the body can contain rapid cell growth rendering it harmless until it can dissolve it and flush it out of the body. To go in and puncture this containment that the body has made with a needle almost invites the cancer cells' reproductions to transgress the containing barrier.
Magnetic Imaging Resonance & Computerized Tomography Scan
The MRI and CT scans are pretty well-known as far as cancer-diagnostic procedures. Both procedures use computers to create a three dimensional or cross sectional image of the internal organs. These tests are effective in identifying abnormal masses or growths but they cannot distinguish a benign growth from a malignant one. Therefore, they are usually used after a biopsy has been done in order to investigate any additional masses that may be the result of metastasizing. Due to the cost and inadequate findings one receives from an MRI or CT scan they are usually recommended only if needed. Therefore patients should be very proactive in determining how real the need is for these procedures.
Urodynamic Tests
These tests are done to investigate issues that appear to be primarily urinary. The Urodynamic tests measure the bladder pressure and urine flow rate. The patient will urinate into a special device which records how quickly the urine flows and how many seconds it takes for the peak flow rate to be reached. An additional urodynamic test may be implemented to measure the amount of urine left in your bladder after urinating.
Abdominal Ultrasound Exam
Ultrasound technology is best known for its usage during pregnancy. Odds are any new or expecting parents are familiar with this procedure because it has become almost mandatory and doctors pressure mothers to get ultrasounds to check on the progression of the fetus. The ultrasound exam in prostate cases is done basically the same way: a gel is applied to the patient's lower abdomen and a handheld transducer is swept across the lower abdomen to acquire a picture of the entire urinary tract. This helps the doctors determine any damage in the upper urinary tract that has resulted from urine blockage at the level of the prostate.
Cystoscopy
Cystoscopy is a procedure so invasive that even reading about it makes men cringe and weak at the knees. In it the penis is numbed so that a surgeon can insert a small tube through the urethral opening at the tip of the penis. This tube, or cystoscope, contains a lens and a light system which allows the doctor to see the inside of the urethra and the bladder. The doctor can then determine the location and the degree of the obstruction.
Documentation
The most common system of documentation in the diagnosis process is known as the TNM- stage method (TNM stands for Tumor - Node - Metastasis). It allows doctors to categorize and communicate the degree at which a tumor has grown in the prostate. The problem is that most laymen or patients are not aware of the meanings behind this system so it enters into the medical jargon that is thrown at the patient in a time of fear and worry. The tumor is assigned a stage between T1 and T4. (See table)
Caption to Table - The TNM Method is the most common form of documentation used to categorize the diagnosis of prostate issues. With more and more cases of prostate issues, more and more are going for routine checkups. It's important that these men educate themselves on the language, procedures and treatments that doctors are prescribing for the various degrees of prostate disease.
An example of a category is TbN+ meaning that the tumor has not only invaded structure below the prostate but the lymph nodes have also been tested positive for cancer. Clinical staging is not exact and is open to human imperfection. The TNM-staging system is the most widely used and relied upon system. It is currently preferred over the Gleason grades which is an older documentation system which assigns a number between 1 & 5 depending on the irregularity of the shape of the cancer cells of the prostate gland under the microscope.
Treatment
The important thing to remain focused on when determining a course of action when there are signs of prostate issues is "What are the possibilities of the next step once I have been diagnosed?" and "How effective will they be?" Countless people have fallen victim to medical doctors who were not as concerned with their patient's health as they were with the opportunity to profit by conducting or having a medical procedure or surgery executed. There are many medical doctors who are interested in helping people and even they will expose that there are medical doctors who are more interested in profit. They will tell you that that the dose is low in most cases the potential side effects and the level of intrusion, danger and discomfort that comes from many of the above methods of diagnosis outweighs what can be done even in the case that those tests effectively conclude that one has prostate cancer.
Active Surveillance or Watchful Waiting
For this unfortunate reason in addition to the fact that the majority of prostate cancer cases are silent many doctors prefer the watchful waiting technique of treatment and diagnosis. Most all doctors will recommend some form of effective diagnosis for BPH or Prostatitis considering that these, as stated above, can be treated at a satisfactory level with antibiotics or other methods short of surgery.
Chemotherapy
Chemotherapy is a method of cancer treatment that is preferred for cancer cells which have metastasized because it is effective throughout the entire body where many other treatment methods such as surgery are effective only locally. The drugs used circulate through the body by the circulation system and kill any rapidly growing cells. This becomes an extreme danger because not only cancerous cells are killed but also healthy non- cancerous cells. In order to minimize this danger chemotherapy has become a science in itself where doctors carefully control the dosage of the poisonous drugs they are putting in the system. This way they are hoping enough not to kill the host while high enough to be effective in killing the reproducing cancer cells. Supportive medication is also given to further help offset the side effects caused by the drugs. Common side effects are fatigue, nausea, vomiting, diarrhea, hair loss, and increased susceptibility to infection. Chemotherapy drugs can be taken either orally or intravenously. Some oral drugs can be administered at home while many drugs must be given at the doctor's office or medical clinic under professional supervision.
Cryoablation
Cryoablation is a form of controlled freezing of the prostate gland in order to destroy cancerous cells. The freezing process is very damaging not only to the cancerous cells but also on many levels: molecular, cellular and to the whole tissue structure. In order to attempt to control the damage done, doctors control the rate of temperature reduction after the initiation of freezing as well as the time cells remain frozen. The heating rate in the thawing process is also extremely dangerous and if not done carefully can be disastrous. This process is very dangerous, even imagining freezing a part of our body with enough intensity to freeze internally is almost unfathomable. The damage done to the cancerous cells in the prostate, or even the cancerous and healthy cells of the prostate cannot be controlled. In cryoablation the surrounding tissue and the capillaries of the area are damaged due to inadequate blood supply. The freezing process starves the cancerous cells but also the live, healthy tissue of that organ and its surrounding areas.
After surgical freezing, a catheter is installed and urination does not normally resume for ten to fifteen days. Once there is proof of regular urination and emptying of the bladder the catheter is removed. Other after- effects are general fatigue, urethral discharge, swelling of the scrotum, numbness at the tip of the penis, passage of flecks of tissue destroyed in freezing, pain or burning sensation during urination and increased urinary frequency and/or urgency.
As one might imagine, the side effects of such a dangerous procedure are many. Though doctors work to try to improve their cryoablatic technology the fact remains that they are freezing the bottom of the body's trunk, a very crucial part in guaranteeing the proper function and health of the body. One of the most critical side effects is known as urinary rectal fistula when a channel is created between the prostate or the bladder and the rectum and may cause diarrhea due to urine in the rectum and possible severe infection due to bacteria in the bladder. Other side effects are erectile dysfunction, urinary incontinence, urinary retention requiring transurethral resection of the prostate and testicular inflammation. Side effects that are more rare are prostate abscess and permanent penile numbness.
Hormonal Therapy
Doctors may recommend hormonal therapy if the cancer is at an advanced stage and is spreading. Hormonal therapy works on the idea that by reducing the hormone testosterone that feeds the cancer the cancer can be controlled. This treatment however does not cure or rid the body of cancer. Though about 85 - 90% of patients do witness shrinking of their cancer unfortunately these positive effects only last between twenty-four and thirty-six months. Patients must weigh the benefit of stopping the progression and shrinking the cancer for two to two and half years against the side effects and consequences of the procedure.
The body is deprived of the hormones which the cancer feeds off of in three different methods. The first is surgery in which the patient is castrated. The testicles are responsible for 95% of testosterone production. The second is chemical castration. A choice of synthetic agents which block natural hormone production are injected into the bloodstream every three or four months. And the last is a mixture of the aforementioned procedures. Side effects of these procedures include: nausea and vomiting, hot flashes, anemia, lethargy, osteoporosis, swollen or tender breasts, erectile dysfunction, and of course castration.
Radiation Therapy
Radiation therapy is a common choice for patients who have a localized cancer. Radiation can be done either externally or internally. External beam radiation treatment or EBRT uses high-powered x-rays to kill cancer cells. After doctors map the exact area of the cancerous mass, using computer imaging software they find the best angles to aim the beams of radiation. This is in hopes of cutting down the damage done to surrounding areas by the laser beam which will be destroying the cancer. Treatments are usually five days a week and last two months. Each treatment is no longer than 10 minutes but side effects are many. Internal radiation therapy surgically installs radioactive seeds inside the infected area directly near the tumour. This implantation is also known as brachytherapy. The 40 to 100 rice-sized seeds deliver a higher dose of radiation than do the external beams, but over a substantially longer period of time. It is used with small and lower grade cancers. The seeds do not have to be removed after they stop emitting radiation, which is usually in a year's time. Side effects for both procedures include urinary slowness and frequency, red-brown urine or semen, impotence, loose stools, rectal bleeding, discomfort dur- ing bowel movements, rectal urgency, pain, swelling and bruising of the scrotum and/or penis and erectile dysfunction.